

It appears the critics finally got to the U.K. Health Security Agency (UKHSA). The new Vaccine Surveillance report, released on Thursday, has been purged of the offending chart showing infection rates higher in the double-vaccinated than the unvaccinated for all over-30s and more than double the rates for those aged 40-79.
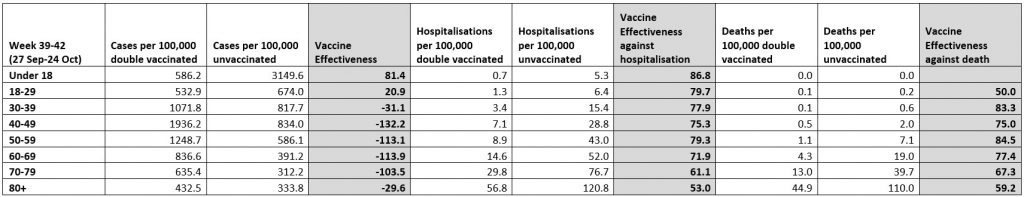
In its place we now have a table similar to the one below that I have been producing for the Daily Sceptic each week (though without the vaccine effectiveness estimates), and a whole lot more explanation and qualification.
Here are our updated charts of unadjusted vaccine effectiveness over time from real-world data in England.
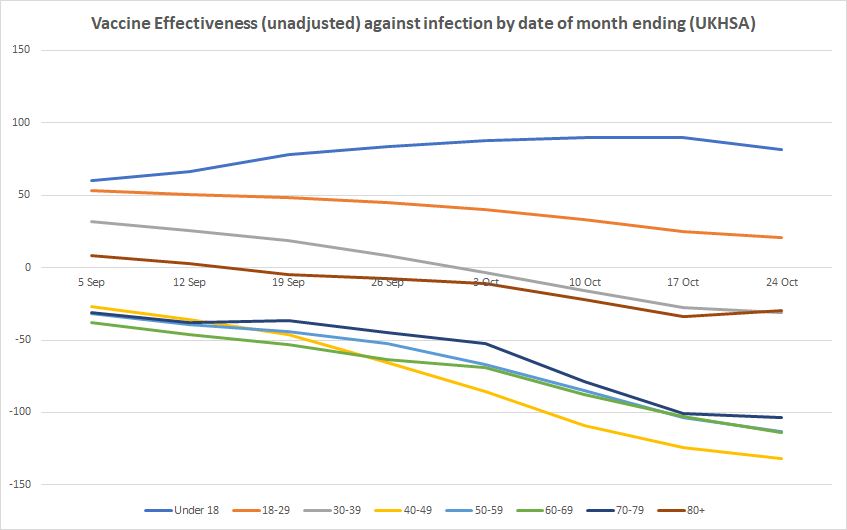
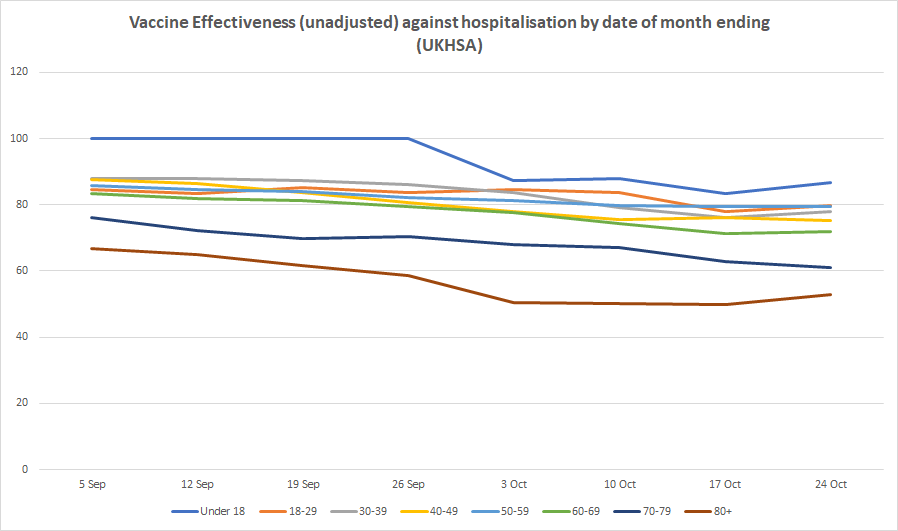
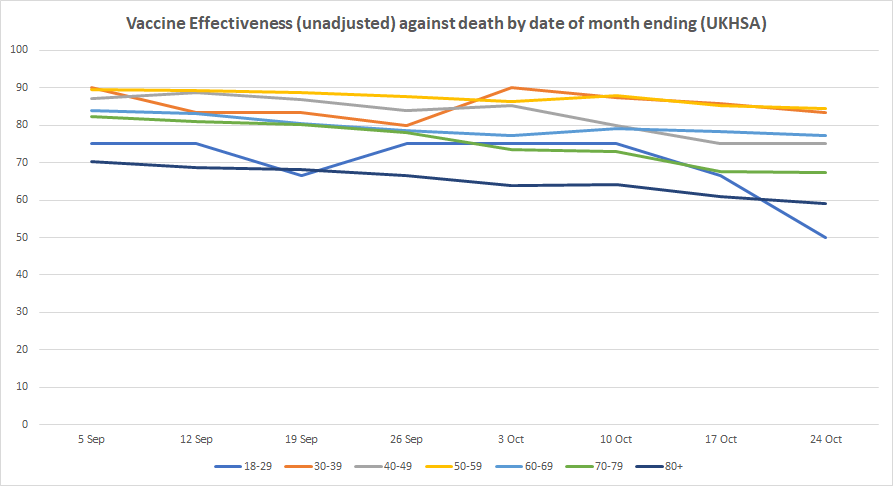
The figures this week continue to worsen for the vaccinated, with unadjusted vaccine effectiveness against infection hitting minus-31% for people in their 30s, minus-132% for people in their 40s, minus-113% for those in their 50s, minus-114% for those in their 60s, and minus-104% for those in their 70s. For those over 80 it rose slightly to a still abysmal minus-30%, from minus-34% last week. Vaccine effectiveness remains positive for those under 30, though for 18-29 year-olds it slipped again to just 21%. It is still highly positive for those under 18, though dropped slightly for the first time to 81%, from 90% the previous week. Vaccine effectiveness against hospitalisation and death remained largely stable this week, meaning there’s no sign yet of the sharp decline found in the recent Swedish study.
It was welcome to see the UKHSA robustly defend its use of the NIMS population data against the criticisms levelled at it by, among others, David Spiegelhalter, who called it “deeply untrustworthy and completely unacceptable”, with the higher infection rates in the vaccinated “simply an artefact due to using clearly inappropriate estimates of the population”. The report counters:
The potential sources of denominator data are either the National Immunisation Management Service (NIMS) or the Office for National Statistics (ONS) mid-year population estimates. Each source has its strengths and limitations which have been described in detail here and here.
NIMS may over-estimate denominators in some age groups, for example because people are registered with the NHS but may have moved abroad, but as it is a dynamic register, such patients, once identified by the NHS, are able to be removed from the denominator. On the other hand, ONS data uses population estimates based on the 2011 census and other sources of data. When using ONS, vaccine coverage exceeds 100% of the population in some age groups, which would in turn lead to a negative denominator when calculating the size of the unvaccinated population.
UKHSA uses NIMS throughout its COVID-19 surveillance reports including in the calculation rates of COVID-19 infection, hospitalisation and deaths by vaccination status because it is a dynamic database of named individuals, where the numerator and the denominator come from the same source and there is a record of each individual’s vaccination status. Additionally, NIMS contains key sociodemographic variables for those who are targeted for and then receive the vaccine, providing a rich and consistently coded data source for evaluation of the vaccine programme. Large scale efforts to contact people in the register will result in the identification of people who may be overcounted, thus affording opportunities to improve accuracy in a dynamic fashion that feeds immediately into vaccine uptake statistics and informs local vaccination efforts.
Much less welcome was the report’s reinforcement of the claim that its data should not be used to estimate vaccine effectiveness. Earlier in the week, Dr Mary Ramsay, Head of Immunisation at the UKHSA, had said: “The report clearly explains that the vaccination status of cases, inpatients and deaths should not be used to assess vaccine effectiveness and there is a high risk of misinterpreting this data because of differences in risk, behaviour and testing in the vaccinated and unvaccinated populations.” I had pointed out that this was false, the report did not “clearly explain” that its data “should not be used to assess vaccine effectiveness”. Rather, it said it was “not the most appropriate method to assess vaccine effectiveness and there is a high risk of misinterpretation”, which (correctly) leaves open that it can be used for this purpose provided the risks of misinterpretation are addressed.
Now, though, the text of the report aligns with Dr Ramsay’s statement. It says: “Comparing case rates among vaccinated and unvaccinated populations should not be used to estimate vaccine effectiveness against COVID-19 infection.”
It is difficult to overstate how outrageous this is. It amounts to Government attempting to redefine a basic concept of immunology, vaccine effectiveness, because it is not currently giving the ‘correct’ answer for the Government’s narrative. It is in fact a false statement. Comparing case rates among vaccinated and unvaccinated groups not only may be used to estimate vaccine effectiveness, it is the definition of vaccine effectiveness, namely the reduction in infection rates in the vaccinated compared to the unvaccinated. Of course, any biases in the data ought to be identified and, where possible, adjusted or controlled for. But that doesn’t mean population data “should not be used” to estimate unadjusted vaccine effectiveness, as though such an estimate tells us nothing useful and is wholly misleading.
The absurdity of this thinly-disguised attempt to throw a sheet over unfavourable data is shown up by the fact that the reasons the UKHSA gives for the estimates being invalid are completely different to the main points its critics are making. Critics like David Spiegelhalter and Leo Benedictus (of Full Fatuous) are primarily concerned with alleged shortcomings of the population data, arguing that ONS data should be used instead. But, as noted, the UKHSA does not accept this criticism and defends its use of NIMS population data. In a normal world, this would mean that, with the main criticism dealt with, we would go back to using the data to estimate vaccine effectiveness.
But no, for UKHSA has another, completely different reason why it deems it invalid to do so. The population data, it explains, gives only “crude rates that do not take into account underlying statistical biases in the data”:
There are likely to be systematic differences in who chooses to be tested and the Covid risk of people who are vaccinated. For example:
• people who are fully vaccinated may be more health conscious and therefore more likely to get tested for COVID-19
• people who are fully vaccinated may engage in more social interactions because of their vaccination status, and therefore may have greater exposure to circulating COVID-19 infection
• people who are unvaccinated may have had past COVID-19 infection prior to the four-week reporting period in the tables above, thereby artificially reducing the COVID-19 case rate in this population group, and making comparisons between the two groups less valid COVID-19 vaccine surveillance report – week 43These biases become more evident as more people are vaccinated and the differences between the vaccinated and unvaccinated population become systematically different in ways that are not accounted for without undertaken [sic] formal analysis of vaccine effectiveness.
This is all unquantified, and the claim at least that it is vaccinated people who are more likely to engage in social interaction is questionable, as anyone who chooses to remain unvaccinated (as opposed to having a condition that makes vaccination inadvisable) is more likely to be relaxed about catching coronavirus (not least because, as per the third bullet point, they may already have had it).
Besides, as I’ve noted before, we don’t need to guess at how large these biases might be, because we can look at the unadjusted and adjusted figures for other population-based studies, like this one in California, and see that the differences are typically very small. While there may be more bias in the England data than the California data that needs adjusting for (why doesn’t UKHSA just get on and do this?), that is no grounds for claiming that the unadjusted estimates tell us nothing of value and “should not” be made, as though we must assume any adjustments will be large.
Furthermore, it is not as though formal studies do always control for these things anyway. A new study in the Lancet from Imperial College London estimates vaccine effectiveness against transmission by looking at infection rates in household contacts who are vaccinated and unvaccinated (and finds the vaccines do very little). But the study makes no attempt to control or adjust for previous infection or behaviour differences. If Imperial College can publish a peer-reviewed study estimating vaccine effectiveness without addressing these forms of bias, why should others be prohibited from estimating unadjusted vaccine effectiveness without adjusting for such biases? Thus the concern about biases starts to appear more like a form of message control, of providing a pretext to forbid unauthorised people from making use of the data, than a genuine issue.
On one level, of course, we can just ignore the UKHSA’s false claim that a comparison of infection rates in the vaccinated and unvaccinated “should not be used” to estimate vaccine effectiveness, and estimate it anyway. But actually we can’t just ignore it. The Daily Sceptic has already been ‘fact-checked‘ by Full Fatuous over this, and such ‘fact checks’ are used by technology and media companies and even regulators to decide what they will censor or permit. This has a chilling effect on people’s willingness to report on the data.
What ought to happen now (though won’t) is the UKHSA should remove the false claim that a comparison of infection rates among vaccinated and unvaccinated populations “should not be used to estimate vaccine effectiveness” and start to do the honest thing and include estimates of unadjusted vaccine effectiveness in the report itself, just as it includes unadjusted estimates of the secondary attack rate based on raw data – if it can do one, why not the other? It should also provide adjusted estimates based on its own analysis. Indeed, back in the spring when the vaccines appeared to be highly efficacious, PHE would sometimes include its own adjusted estimates of vaccine effectiveness, even when it only had ‘low confidence‘ in the findings. Why not go back to doing that? Or are they only interested in doing this when it gives the ‘right’ answer? It’s beginning to look that way.




Discussion
Comments
This week across the site:
To join in with the discussion please make a donation to the Daily Sceptic.
Profanity and abuse will be removed and may lead to a permanent ban.
Is the author aware that minus-132%, means that he is saying they are +132% effective?
A repeated mistake, but not important in comparison to the fact that the article is clearly misleading. Any readers who are actually interested should read the actual vaccine surveillance report.
Anyone else getting liars fatigue, I know I am. I know what the reality is and yet we are continuously fed lies. I don’t read msm or listen to it. Sadly those around me repeat the gov’t mantras over and over and over. I sit quietly and swallow the nonsense.
Most of us can be honest and say today, the only people we know with Covid are the double jabbed. It really is that simple.
Currently I know of 4 vaccinated people with serious hepatic disorders and another 8 with recently diagnosed breast cancer. No proof of course that the vaccines were to blame but sometimes you just get a gut feeling about things.
All the people I know that were vaccinated were immediately eaten by sharks.
I read one of Will Jones’s earlier articles. It was about teenage boys’ mortality and vaccines. It was a completely bogus analysis, some of which he retracted when his errors were pointed out. I have read this latest analysis. It is a garbled rehash of what is a very clear and open report from the HSA. I am never quite sure if Mr Jones genuinely believes the conclusions he draws from his reading of raw data or that he feels the need to deliberately confuse the readers of the dailysceptic in order to frighten and mislead them. He certainly appears to be on a bizarre evangelic mission of some sort. My main complaint about his work are his insane extrapolations and his misunderstanding (or perhaps deliberate misinterpretation) of stats and sub-sets. You cannot properly understand the HSA raw data unless you understand the context. ie you need to see them in relation to their percentages to work out the related risk factors. What these figures show quite clearly is that vaccinations protect all ages against the risk of catching covid, (likely) the risk of passing it on, the risk of hospitalisation, the risk of death. I much prefer my chances… Read more »
It would be very helpful to me, and I suspect to many other readers, if you were to provide at least one example each of an insane extrapolation made by Mr Jones and of a misunderstanding of his.
OTOH, it’s also helpful if such texts really contain nothing but strongly judgmental adjectives attached to a person with no shred of an explanation why they’re being attached. That’s the mark of a content free propaganda text and one presumably written by a professional in this ‘craft’ with few – if any – other skills, including reading comprehension. There’s no reason why someone would be scared by texts as dry and factual (no criticism intended) as these usually are.
“….as the real world data rolls in….”
Most of us here are not statisticians and I must admit that my eyes glaze over when I read some of the articles posted here which contain a lot of statistics. However, I do have my own “real world data” at my disposal. These are my findings:
I knew of no-one last year who was either hospitalised or died from Covid.
I only knew two people who “tested” positive and only one of these showed any symptoms. His doctor provided him with antibiotics in case it was a chest infection as, apart from a positive “test”, there was no physical examination or other clinical evidence- something which the WHO, the CDC and the U.K. government stated should be used alongside a positive “test” result.
This year, I know 10 people who have tested positive having been double jabbed. They have not been particularly poorly, just a sniffle, but then again we are dealing with a more virulent but far less dangerous variant this year and using last year’s weapons to fight it.
Having read up about the leaky vaccines (yes, I know!) some of which have been banned by certain countries for age… Read more »
And, of course, there are the results of FOI requests to local authorities that show figures from the past five years of burials and cremations – there is very little difference.
I wonder why you come on to this site and read articles which you obviously disbelieve and wish to denigrate. I’m sure there are many other sites that would suit your mindset far more comfortably.
Some people want to correct misinformation. Some people want to believe it.
Your analysis of this author’s articles is very valid. His conclusions are clearly untrue and unjustified.
I wouldn’t hold your breath on waiting for the admission of error. I’m sure he is aware of his false analysis.
Those in power/with a vaccine to sell have cleverly rewritten the narrative of what the vaccine was originally intended to do. If you read the AstraZeneca and Pfizer papers claiming “efficacy” and “safety”, you will see that efficacy was predicated on lower POSITIVE PCR TEST numbers in the vaccinated group. I. E. lower chance of getting coronavirus. I don’t see this turnaround being challenged anywhere yet is surely one of the biggest lies (of so many) being perpetrated.
The key issue here is reporting of cases. How are the cases reported? are the unvaccinated less likely to report cases? Of course by the time an unvaccinated person gets to hospital they have ‘no choice’ but to report their status. If I got covid I would be in no rush to report it, wouldn’t know how to and probably wouldn’t see the need.
I watched on Netflix again last night the film ‘V for Ventetta’, a look into the dystopian country we could become.
It’s chilling how this film portrays an autocratic state, controlling its people through propaganda, fear, disinformation, and finally violence.
Is this the way this country is heading? It would appear so, a state ruled by those that are elected to serve us.
The ‘Nudge Unit’ is very effective at getting this country to do the government’s bidding, and so many don’t even know of its existence. Perhaps it could be the subject of an DS article. As I understand it this entity is a limited company owned jointly by government and privately. It works in all government departments to ‘modifying’ the public’s behaviour to get us to comply on big issues like Net Zero, the NHS and C-19. It is so effective. The work of this ‘unit’ needs much more publicity.
If you’ve not seen this film, watch it, it’s a little weird, but the underlying message is stark.
I haven’t watched it yet (only came today) but the film entitled ”One by One” with Rik Mayall (2015) seems as though it might mirror some of today’s ‘problems’.
Reality based community
Faith, Certainty and the Presidency of George W. Bush
The standard definition of efficacy is only half the picture, as it’s a measure of relative risk reduction
The NHS commercials pushing vaccines and boosters must be costing the Government millions (really costing us the taxpayers) so it makes sense they want to hide this truth about vaccines. I did the first two, and am now finished, with all of this. No booster.
With no booster your Vaccine Pass will become invalid. What then? How about a protest round at the UKHSA headquarters? Just an idea.
Good decision. Welcome.
There aren’t ‘higher rates’ in thee jabbed… if many of the jab are ending in hospital is because the phoney jab is gradually destroying their immune systems.
ONE minute after the untried injection, you start to D I E! ”Forbidden knowledge. Medical Bombshell: Pfizer Vax Attacks Human Blood Creating Clots Under Microscope”.”.
John Dee’s Almanac – Telegram | # NHSUK: Initial Results From Simulation Study
In the last few posts we’ve chewed the cud over the non-random nature of data and the multitude of biases that we cannot possibly hope to account for, and the group has been instrumental in helping me formulate a whole new approach for solving what appears to be an intractable problem. Until we solve these fundamental problems we cannot say anything about vaccine benefit or disbenefit. Well actually we can, but what we say isn’t going to be worth tuppence!
Whilst sitting in my battered Land Rover watching masked shoppers yesterday I hit upon the idea of randomising the data and comparing randomised datasets to the original. This morning I narrowed the scope down to investigating the EPR of 9,783 in hospital deaths since 8th December 2020 for a sizeable NHS Trust that must remain unnamed. The EPR enables me to know if and when these people were vaccinated prior to death and whether their death was associated with a diagnosis of COVID. It is thus a simple matter to cross-tabulate vaccination status with COVID status to see how the cookie has crumbled in terms of crude… Read more »
The interesting bit about Spiegelhalter’s statement is the unacceptable. Acceptable is not a scientific criterion: Facts don’t care about being accepted and the purpose of science is to determine facts. Hence, what Spiegelhalter considers unacceptable is either false. If so, it should be discared. Or it’s true. And then, he’s by definition a maniac, ie, someone who refuses to accept reality.
Damage control has already started –
https://www.dailymail.co.uk/health/article-10145637/amp/Unvaccinated-Americans-previously-infected-COVID-19-risk-vaccinated.html
CDC claims if you already had the virus and aren’t jabbed, you are five and a half times more likely to wind up in hospital.
Propaganda, you love it
When you get to the half time, do you get a break and some orange to suck?
“CDC claims if you already had the virus and aren’t jabbed, you are five and a half times more likely to wind up in hospital.”
Not if you get treated early by these medics and their peers:
https://youtu.be/4IeVy7jQoz0?t=1842
Even without such a lengthy criticism of their data analysis techniques and caveats, the fact Spiegelhalter chose now to criticise the reports and they removed the chart speaks volumes. If this was an issue, it was an issue with Technical Briefing 1. And yet, as it fit the narrative, it was OK then.
They are laughing at us.
Keep trying the play the game by their rules and eventually you won’t have any data left to analyse at all, only the latest orders to be obeyed without question.
“Comparing case rates among vaccinated and unvaccinated populations should not be used to estimate vaccine effectiveness against COVID-19 infection.”
This is the most illogical, unscientific thing I’ve ever read, what a complete moron.
At some point we’re all going to have to face the fact we no longer live in a democracy as we previously understood it, but a post-truth hellscape where the regime can routinely change the definition of words like “vaccine” and “pandemic” and “vaccine efficacy” to avoid awkward questions about its murderous policies. Other words it may soon redefine could include “justice” and “trial” and “death sentence”
Terrorist = anyone who criticises the regime
Also: has anyone noticed the (laughable at best of times) level of protection against infection seems higher (but still a laughable level compared to the protection classical vacciens give against other disease infection) in the groups where covid largely is spreading and in the groups where less proportion of the group have been vaccinated? Seems a little bizarre but might be worth something as an observation to try to come up with a proper explanation as to why effectiveness manages to become negative.
Even if the unvaccinated groups were totally immune to infection on the basis of surviorship bias / thanks to earlier immunity, it would not be an argument against vaccination. Causation is difficult to understand, isn’t it?
It’s not a vaccine though is it. Vaccines provide immunity, this shot does nothing of the sort. You can’t even argue that it reduces hospitalisation or death, because it clearly doesn’t.
Put these “guys and one lady” in charge:
https://youtu.be/4IeVy7jQoz0?t=1842
As you point out the current vaccine, which allows long term circulation of Covid-19 in the vaccinated, must lead to natural immunity in the un-vaccinated population.
This is an irrefutable argument against vaccine passports and coercion of the un-vaccinated community.
Whether this inevitable outcome is an argument against the use of the current vaccines depends on whether the additional protection provided by post vaccination infection is as good as that seen in the un-vaccinated post infection.
Recent UKHSA reports indicating of weaker antibody response to N-proteins in the infected vaccinated and the fact that boosters are needed so soon after decline in the circulating exosomes due to vaccination may already provide an indication as to the answer.
Why inject someone with something that’s experimental against a reported disease with an incredibly high survival rate. Rates no different to the flu. Its a nonsense
Well the obvious answer is that the vaccines do nothing and the unvaccinated aren’t stupid enough to get tested.
Pssst… the Covid ‘vaccines’ are f*cking useless… pass it on…
Typos corrected:
the Covid vaxxines are worse than f*cking useless
Quite honestly, for these covid vaccines effectiveness clearly is not related to the ratios of cases per population among the vaxxed and unvaxxed, they never have worked against infection and their initial trials weren’t even designed with this in mind. The effectiveness must surely be the statistics for hospitalisations or deaths, the trials afterall were set up with the intended outcome being that a lower proportion people who had taken the vaccine would get hospitalised. We’ve yet to see if this effectiveness drops off as that Swedish study shows, but the one solid fact we have is that vaccines clearly do not stop the spread (with cases now stable at arund the highest peaks of the waves we clearly haven’t wiped the virus out) so we need to simply tolerate coid and live normally without tyrannical bullshit imposed on us. Reduced hospitalisations and deaths should make the virus easier to tolerate, but even if vaccine effectiveness of this kind wanes, we still have to tolerate the virus, any alternative is too costly in terms of things which matter (civil rights, the economy, mental health…).
An interesting nuance to this new data is that for some reason they’ve removed about 100,000 (nearly half) of the individuals from their <18 double-vaccinated data. There is no explanation for this. I’d note that they don’t offer this on a plate — you have to calculate it from the data they provide.
It does have a significant effect on the estimates of vaccine effectiveness for this group (c. 90% to c. 80%).
It is likely that they’re correcting an error that has been present in all prior UKHSE reports — IMO it is a bit naughty of them to not explain this change.
Yes, I’d noticed that. See the attached where I’ve highlighted the change.
The raw rate of infections in the single vaccinated under age 18 age group is 2,727 per 100,000 vs 3,150 per 100,000 in the unvacccinated.
That’s at a time that the number in the single vaccinated category is changing quickly, so some caution there in comparing figures as the denominator is more unreliable in this age group. But not much difference.
The 586 per 100,000 rate in the double vaccinated looks like unreliable data because it is based on an unreliable very small number of people as this change shows.
So it is important to say that the apparent efficacy at preventing a positive test in the double vaccinated under 18s should be ignored because of these significant data issues.
So, in the worst case (Ferguson-style modelling), the data suggests that around 95,000 double stabbed under 18s died between weeks 42 and 43?
Ha ha!
But being serious it shows the potential for NIMS to overcount the number of double vaccinated.
The political narrative/Spiegelhalter implied assumption is that the number vaccinated is 100% correct and the total NIMS population is too high and so the potential overstatement of the NIMS population relates solely to an overstatement of the unvaccinated number and so in the ‘case’ table an understatement of positives per 100,000 in the unvaccinated.
This shows why this assumption can’t be made. There might be double counting of the vaccinated in other age groups too going on in the NIMS database.
On the reddit site, poster “uncivil” is working on PHE data systems and had identified massive over-counting of vaccine taking individuals, perhaps why there is nervousness about introducing the Pass.
Thanks. Very interesting. I’ll have a look.
Norman Fenton looks at how NIMS works at the operational level in his paper and constructively looks at how vaccinations can be over-recorded or under-recorded on NIMS.
His diagram (attached) indicates how these errors can then feed into the vaccine passes.
If you look at the last 2 PHE (UKHSA) data spreadsheets and compare identical weeks if anything they are slightly increasing their estimate of the unvaccinated proportion for identical weeks. I’ve not checked against the earlier reports to see if it this is part of a continuing trend or not.
But potentially any errors UKHSA are finding are currently not pushing down the unvaccinated proportion it appears, if anything it’s very marginally the other way. Of course the errors they are finding may not be reflective of typical overall errors in the database.
Thanks again. I located this there which is very interesting
https://www.reddit.com/r/LockdownSceptics/comments/plwof5/todays_comments_20210911/hcer9fr/?context=3
https://t.me/s/JohnDeesAlmanac/639
Many analysts around the globe have been struggling with getting a robust answer for vaccine benefit, and like many I’ve been pulling my hair out trying to trap down all the factors. I’ve fallen foul of my own assumptions and methodological limitations many times and two days ago was ready to give up the quest for the Grail.
Keep your fingers crossed that this work passes muster because if it does it can serve as a base method to determine the true impact of COVID as well as the vaccines. The world needs to know if we are heading in the right direction.
Just been reading this Telegram thread- truly heartening to know how many private citizens are crunching the numbers for the rest of us. Glad to know he is in discussions with HART group.
Also watched the latest Irreverends podcast which this week is on Odysee due to the nature of the discussion about the large increase in ‘cases’ since the rollout of the vaccines.
Great article, Will.
The change to them declaring that the figures ‘should not be used to assess vaccine effectiveness‘ is worrying, but not unexpected given the current climate. I’d not fully appreciated the difficulties caused to those wanting to publish fair and reasonable discussion articles of the figures by them making this change, while still supplying the figures themselves.
The implied idea that people who are fully vaccinated are out socialising while the unvaccinated are cowering under their beds is so ridiculous that it is embarrassing to read. Someone earlier described it as Orwellian to read that.
This is not some small effect such as the double vaccinated testing positive at a rate 10% higher than the unvaccinated, but it’s more than double across a range of different age groups. That needs some explaining away if the vaccinated are really less likely to positive, and any explaining away needs to be challengeable.
I also was pleased to see UKHSA defend the use of NIMS. The NIMS English population total of about 62.5 million (21.2 million unvaccinated, 38.0 million double jabbed, and 3.3 million single jabbed), compares with the ONS estimates which might be 56.5 million I think. So there is… Read more »
The jabbed are now justifying their jabs by saying the really bad flu they got could have been worse! They just know …..
Also, the government already adjusts the Yellow Card reporting so it won’t be long before they ban that all together as well as the truth may be harmful to the message.
These UKHSA hospitalisation and death statistics seem to be to be at variance with those recently published by Public Health Scotland.
For the period 25 September to 22 October PHS has the hospitalisation ratio for the over 60s at 90% to 10% for vaxxed/unvaxxed. PHS gives the death ratios for all ages as 85% to 15% for vaxxed to unvaxxed. I got this from The Expose website.
The UKHSA stats are very different to the PHS ones. Which set of figures are the more accurate?
The MHRA website does not attribute a single one of the circa 1700 Yellow Card reported covid vaccine deaths to the jabs.
These statistics show beyond doubt that covid vaccinating children and pregnant women is absolutely wicked. They are, I would say, completely useless, extremely dangerous and intrinsically harmful.
You don’t give a link for your data, but I imagine that the PHS data is overall data; if 90% of the population is vaccinated you’d expect 90% (or so) of hospitalisations in the vaccinated.
The UKHSE data presented in this article is for per 100,000, ie, it removes the effect of the rate of vaccination in the country.
You would expect 90% hospitalisation if the vaccine had no effect on the risk of being hospitalised for the vaxxed. The UKHSA data suggests there is a reduction in risk for them.
The link to The Expose article is : https://theexpose.uk/2021/10/28/85-percent-of-covid-19-deaths-among-the-fully-vaccinated/
To put things in context, the data suggests that around 160 people die with/from/+ve test result covid a week. There are around 10,000 deaths a week from all causes. Where is the sense of proportion?
For the top 5 leading causes of death, there would be around 800 ischaemic heart disease, 500 dementia, 350 chronic lower pulmonary, 300 cerebrovascular, 280 influenza.
Currently Covid with/from vaxx-or-unvaxx is less deadly than influenza.
Many people don’t need the censored data that shows how shite the ‘vaccines’ are – they can see what’s happening to their friends and family. A pureblood friend of a friend noticed that none of her aunts, uncles, etc had had covid until they were double jabbed, and now they’ve all had it. So, according to that data; to get covid – get jabbed
Agree, in one workplace I deal with we had 5 infections from 2020 through to July 2021. Since July, there have been 8. I don’t know the vaccine status of all of them, but at least 90% are double jabbed.
That’s the thing – they may try to hide the data but people can see it with their own eyes.
So in very round numbers, if the shot halves your chances of dying should you be infected by “it”, but doubles your chances of getting infected, isn’t the net result just a big fat zero?
I don’t think so. I believe the stats are of people dying with/from covid (I presume with positive test within 28 days so possibly not that meaningful) expressed as a fraction of the total population. But how much one can really conclude from this is questionable as you would need to adjust for the underlying state of health of the people dying, and also consider that since the mass vaxxing, compared to this time last year, all cause mortality has gone up. I think you’d need to look at how your vaxx status affects your chances of dying of any cause, compared to a similar figure pre-covid.
Net result a big zero?No — that’s only looking at individual level. Because the vaccinated now have much greater infection rates, this then impacts on R; how likely it is for one person to infect another (as they’re more likely to get infected). What’s worse is that case numbers aren’t simply related to infection rates, but are exponential — if you have an increase in infection rate by 50% you’d expect case numbers to triple (roughly).
So, even a small increase in infection risk might have a significant impact on case numbers — maybe you’d expect a western European country that vaccinated early and in high numbers to have surprisingly high case loads…
And the more cases there are, the more hospitalisations/deaths you’ll have. I’d note that these will largely be in the vulnerable groups.
So, we’ve vaccinated everyone only to significantly increase the risks for the vulnerable (compared with only vaccinating the vulnerable).
Furthermore, you’d expect the unvaccinated to be heavily impacted by this — they might be less likely to get infected than the vaccinated, but they do get infected and they do sometimes suffer hospitalisation and death.
So, we’ve vaccinated everyone which has led to increased risks… Read more »
Having been away last week I had the chance to visit a few pubs up north. Couldn’t help but overhear a conversation between 2 tables with one couple saying they’d had the ‘rona but “fortunately we’d had our jabs or it would have been so much worse”.
The list keeps growing.
How do they know it would have been worse? I’ve asked a couple of people who’ve spouted this nonsense and they mutter rubbish about just knowing it would. It seems to be their only defense against the stupidity of getting jabbed.
So far the same crap has spouted by every idiot I know that’s gone down post jab. People are still convinced that the best case scenario for unjabbed cv19 is that you’ll end up in hospital. Why? Because they don’t know anyone that actually had it prior to getting jabbed.
One nugget at work proudly declared last week “I’m starting to think that we’re all going to get it at some point and we’re just going to have to live with it”.
Amazing that it’s only taken 18 months for a highly educated person who spends his day working with complex financial data to work out the bleeding obvious but hopefully it indicates a turning point as none of the other zombies disagreed with him.
They all say that. It’s the mating call of the brain-dead.